

Hospital management & revenue cycle platform · India
The operating system for hospitals that get paid in full.
Clinical operations, insurer rules and the corporate panel on one patient record — so the deductions that cost Indian hospitals lakhs a month are caught at admission, not argued about at settlement.
Send twenty recent settled claims (names removed). In five working days you get back, claim by claim, what each payer took off and why — and which of it Drapto would have caught at admission. Free, under NDA.
Room cap breached · no consent on file
Pre-auth clock at 18h of 24h
Package billed with components
Code in notes, missing from bill
Illustration with sample figures from the Drapto test workspace.
- ABDM · ABHA at the desk
- NHCX · FHIR R4 bundles
- ICD-10 coding engine
- NABH evidence
- DPDP Act 2023
- Indian data centres
- On-premise or managed
Every hospital records what happened. Drapto changes what gets paid.
The platform
One record. Four products. No hand-offs.
Named after the work, not the org chart. Every product writes to the same patient record, so a risk raised at the front desk is still there at discharge.
Revenue integrity
Room-cap proportionate deduction modelled at admission, pre-auth clocks per payer, 24-rule claim scoring and every settlement advice read line by line.
Explore →Clinical & wards
Intake, chart, deterministic ICD-10 coding, rounds and discharge summaries coded before they leave the ward.
Explore →Corporate panel
Eligibility checked at the desk, health-check campaigns and an HR view that shows attendance and cost — never a diagnosis.
Explore →Booking plan
Your own booking page, OPD calendar, walk-in queue, prescriptions in plain words and a day book — with 0% commission.
Explore →NABH, ABDM & NHCX
NABH registers kept from daily work, ABHA linked at registration and NHCX FHIR R4 claim bundles validated before they go.
Explore →Nadi & the agents
Ask your own data in plain words, and let ten scheduled checks raise what needs a human — on your own AI key.
Explore →Who it is for
Built for the people who carry the write-off.
Hospitals
Owners, medical directors and billing managers who bill TPAs, insurers and government schemes.
Explore →Multi-branch chains
One operating picture across branches: leakage by branch, contracts by payer, one record per patient.
Explore →Clinics & doctors
Single doctors to polyclinics who want the desk, the prescription and the money in one place.
Explore →Employers
Companies that want a health benefit their people actually use, with a privacy line HR cannot cross.
Explore →Inside Drapto
The screens your teams open every day.


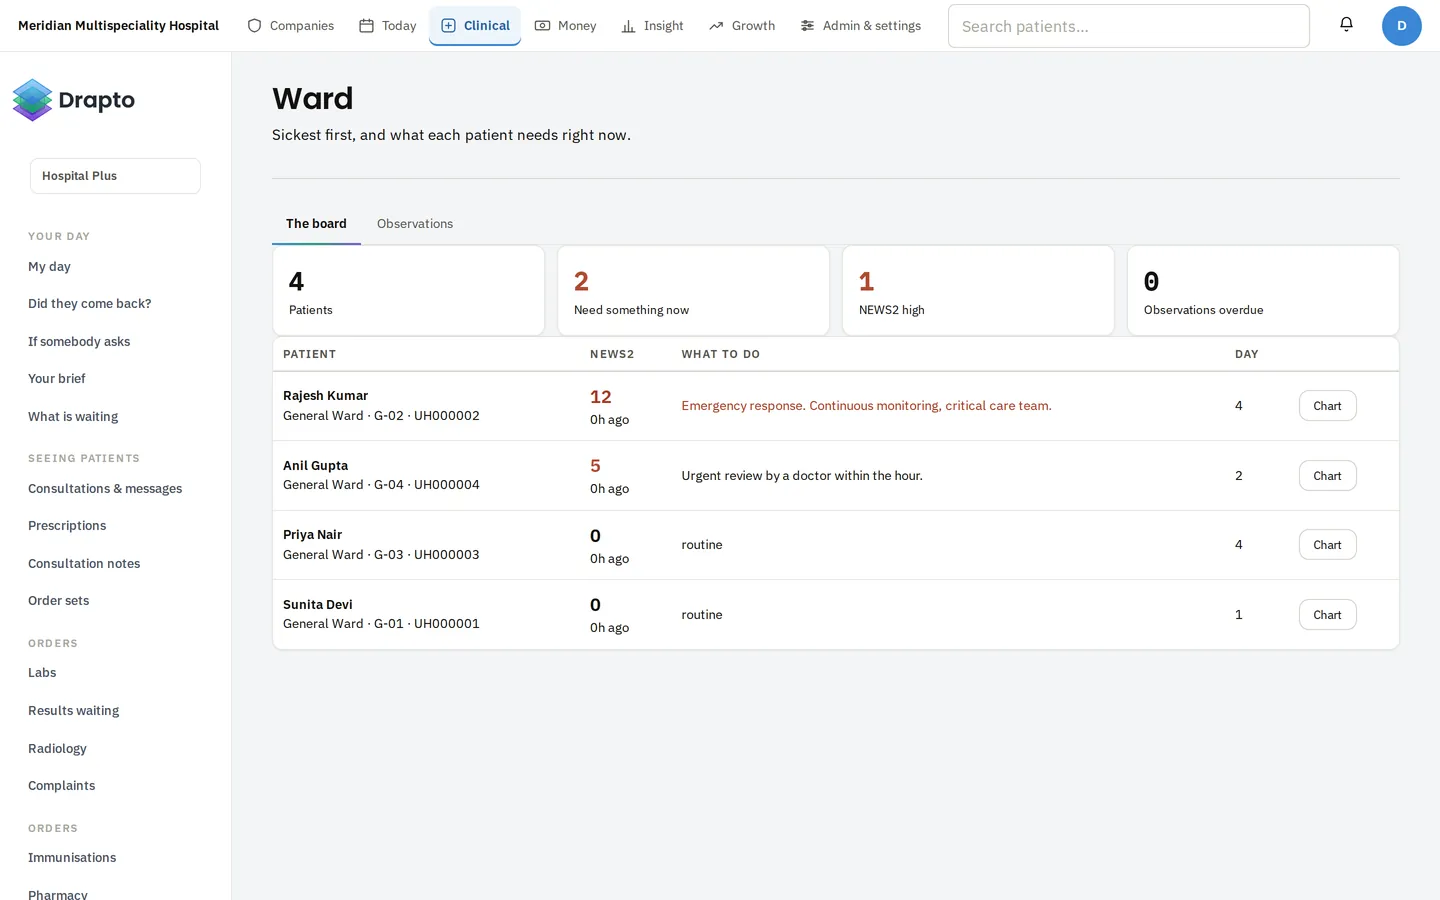
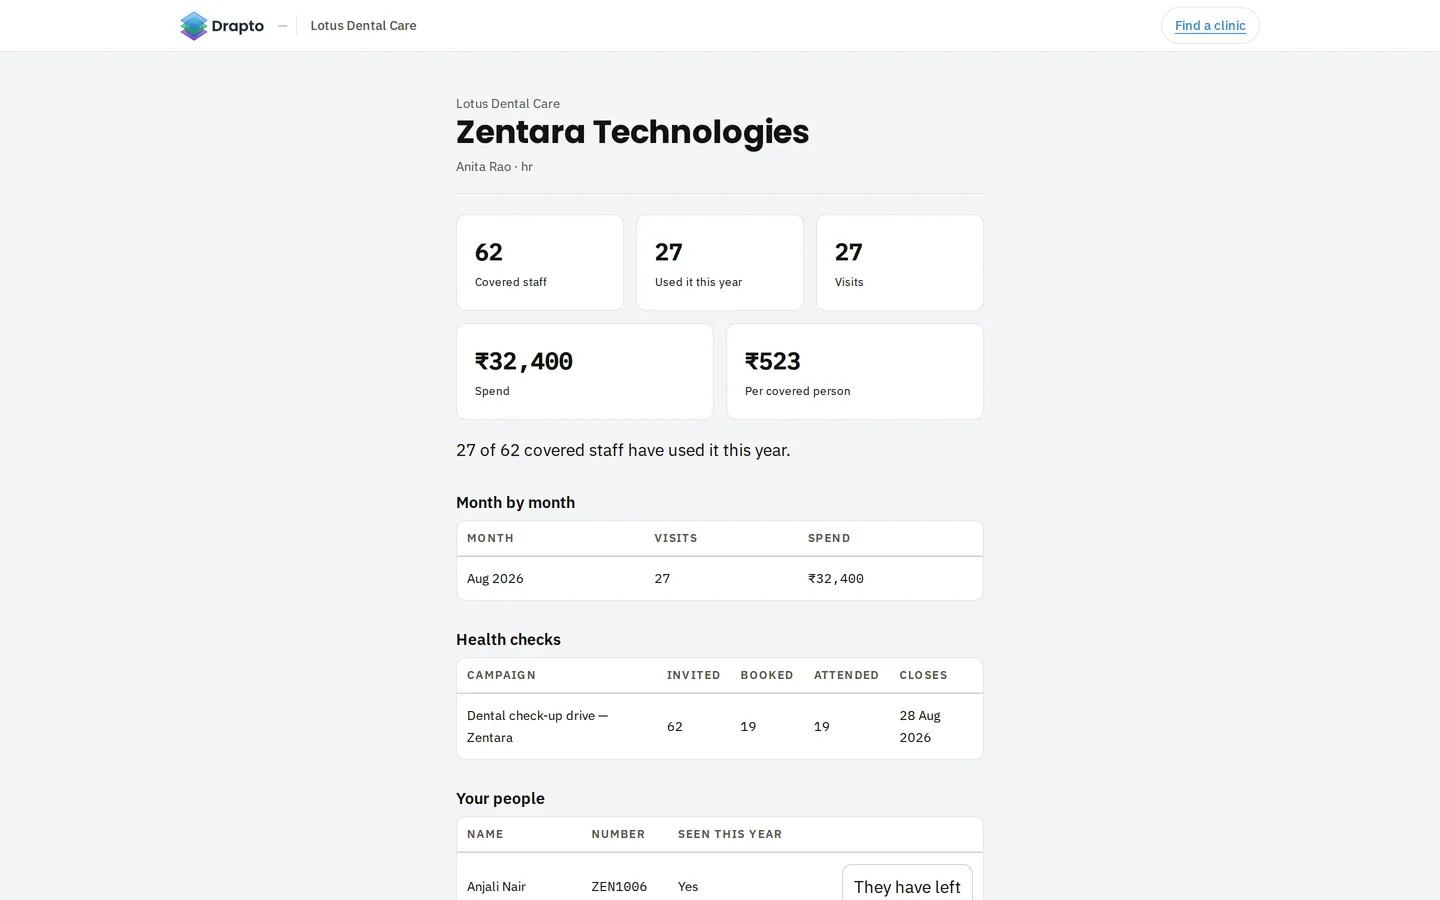
Demo workspace · sample names and figures, not customer data.
Agents on a clock
Ten checks run every night. A person decides.
Not an assistant you have to remember to ask. Scheduled checks over your own records raise what needs attention — and nothing is sent, filed or written off without a named person approving it.
Revenue Leakage Analyst
Finds money already earned and not yet collected — unbilled procedures, write-offs, ageing — and explains why in plain words.
Explore →Doctor Performance Coach
A monthly coaching note per clinician, weighted for patient experience as well as volume. Never a league table.
Explore →Patient Reactivation
Finds lapsed patients by value and recency and drafts the outreach for a person to approve.
Explore →Where Drapto fits
Your HIS bills. An outsourcer chases. Drapto stops the loss before it happens.
Columns describe categories of product, not any one company.
| Your HIS claims module | RCM outsourcing | Drapto | |
|---|---|---|---|
| Room-cap deduction modelled before admission | Rarely | After settlement | At admission, per payer |
| Every settlement line read and explained | No | Sampled, by hand | Every claim |
| Works on top of the HIS you run | — | Yes | Yes — imports from its exports |
| Who keeps the data | You | The vendor’s team | You — your server or ours |
| Connects the employers you treat | No | No | Corporate panel |
| How it is paid for | Licence + AMC | Usually a share of collections | Annual proposal, no share |
The full comparison → · Why an HIS claims module is not revenue integrity →
Deployment
Your server, or ours. Same software.
On-premise
Runs on a single machine in your server room, works through an internet outage and keeps patient data on site. Backups and restore scripts included.
Managed, in India
Hosted on Indian infrastructure, updated and backed up by us, with tenant isolation and a full audit trail.
Explore →Export on demand
Every record, in open formats, whenever you ask. Read how to leave before you sign.
Explore →Across India
17 regions. 102 cities. Every state scheme, mapped.
MJPJAY in Maharashtra, CMCHIS in Tamil Nadu, Aarogyasri in Telangana, Swasthya Sathi in Bengal — each settles claims its own way, and Drapto models each one.
Questions
Asked before every demo.
What is Drapto?
A healthcare operating system for Indian hospitals, hospital groups and clinics: intake, the chart, wards, labs, pharmacy, NABH evidence and a revenue-integrity layer that catches insurer deductions at admission — plus a corporate panel that connects hospitals to the employers whose staff they treat.
Does Drapto replace our HIS or HMS?
No. Most hospitals keep the HIS they bill from and run Drapto alongside it. Drapto reads its exports and adds what it does not do: deductions caught before discharge, settlement advices read line by line, NABH registers kept from daily work.
How is Drapto priced?
By written proposal after a free demo, sized to beds, branches and modules, billed annually in rupees, 18% GST extra. There is no free plan, no public price list and never a share of your collections.
Is it cloud or on-premise?
Both, from one codebase. Run it on a single server in your building — it works through an internet outage — or we run it for you on Indian infrastructure.
Is Drapto an AI product?
Where AI helps. Claim scoring and ICD-10 coding are deterministic and run offline; the assistants run on your own AI key and every figure they show links back to the record it came from.
How long does it take to go live?
Most hospitals are live in one to five weeks. Clinics usually take a few days.
See Drapto on your own payers.
A free 30-minute demo on your room categories, your TPAs and the deductions you see most — then a written proposal.
Questions? enquiry@drapto.com